Thymosin alpha-1 clinical trials
Here the peptide really reached human treatment trials. More evidence brought a less encouraging answer about survival.
Two sepsis trials
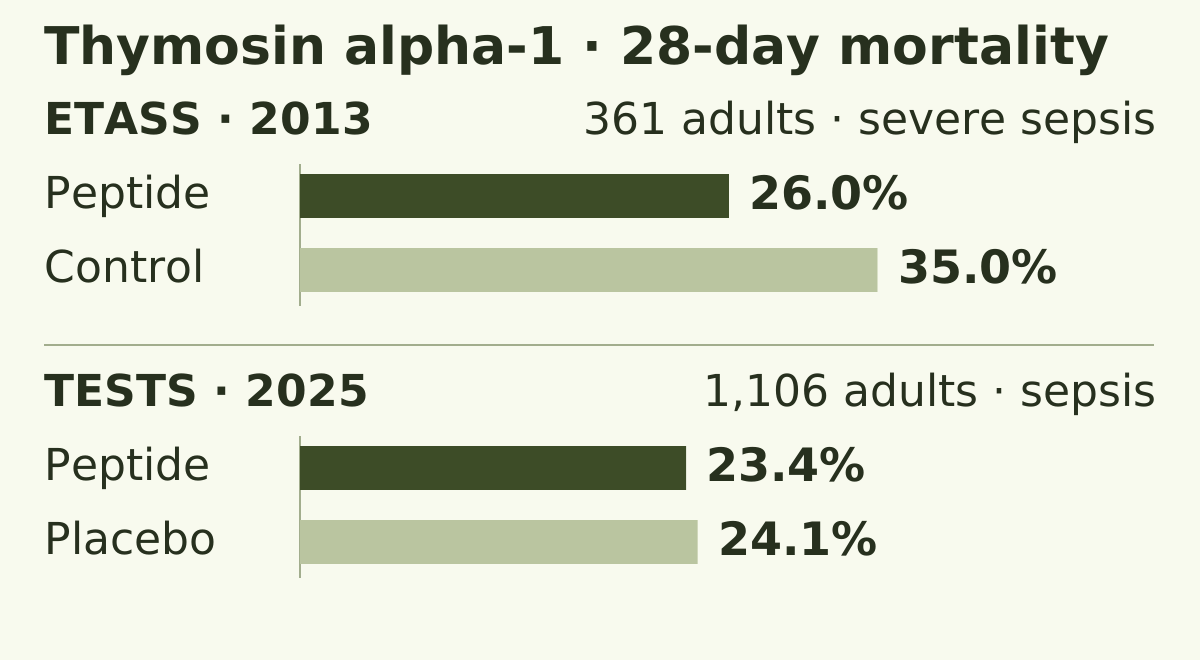
Sepsis is a dangerous body-wide response to infection. The earlier ETASS trial in 361 patients with severe sepsis reported 28-day mortality of 26.0% with thymosin alpha-1 and 35.0% in controls. The comparison of mortality proportions gave P=0.062; a time-to-event analysis gave P=0.049. That statistical disagreement left the apparent survival advantage uncertain.
I understand the appetite for a larger trial after that result; confidence in an established survival advantage would have been premature. In the later double-blind, placebo-controlled TESTS trial, 1,106 adults with sepsis took part across 22 centres. Patients and staff were unaware of treatment allocation. At 28 days, mortality was 23.4% with thymosin alpha-1 and 24.1% with placebo, with no statistically significant difference.
The later result gives the sepsis argument an answer it has to live with. It does not establish a mortality benefit in those patients. Other proposed uses require their own evidence.
COVID-19 patient charts
The retrospective study of 76 people with severe COVID-19 reported mortality of 11.11% among treated patients and 30.00% in the comparison group. It also described increased blood T-cell numbers in people with severe lymphocytopenia, a shortage of these immune cells, and changes consistent with reversal of T-cell exhaustion.
Those observations help explain the biological interest. Treatment was not assigned by chance, so differences between the patients or their care could have contributed to the outcomes. The comparison concerns severe COVID-19, a different clinical setting from sepsis. The papers would make a poor ballot, with votes tallied for or against a peptide regardless of illness or study design.
Immune regulation and cancer research
Thymosin alpha-1 is a 28-amino-acid peptide released from a larger protein. Its synthetic medicine form is thymalfasin. The comprehensive literature review describes effects on cells that recognise threats, present them to other immune cells, and help organise a response. Regulatory pathways can also temper inflammation.
That two-sided biology is more interesting than the phrase immune boost. The desirable response depends on the illness and the state of the immune system. A review of thymosin alpha-1 in cancer therapy examines its proposed role alongside chemotherapy and immunotherapy, drawing on preclinical and clinical work. It is an argument about combination treatment in particular settings, with no basis for a universal cancer claim.

Thymalfasin safety and approval
The review of clinical use reports thymalfasin approvals in more than 35 countries and mainly local irritation, redness or discomfort where injections were given. The United States has not approved thymalfasin for sale as medicine. Experience with a medicine used abroad leaves the identity, content and sterility of a research-grade preparation unresolved.
Community accounts describe fewer seasonal infections, steadier energy, faster recovery or no noticeable change. Complaints include itching or stinging, aches, headaches and tiredness. Those are anecdotal accounts, not clinical evidence, and they cannot establish rates of benefit or harm.
Changing immune activity raises theoretical questions in autoimmune illness and after an organ transplant, where treatment may intentionally suppress immune responses. Pregnancy and breastfeeding safety data are lacking. I question that broad wellness promise: this peptide has specific human results, including a well-conducted trial that disappointed. That record deserves a more exact claim than general resilience.